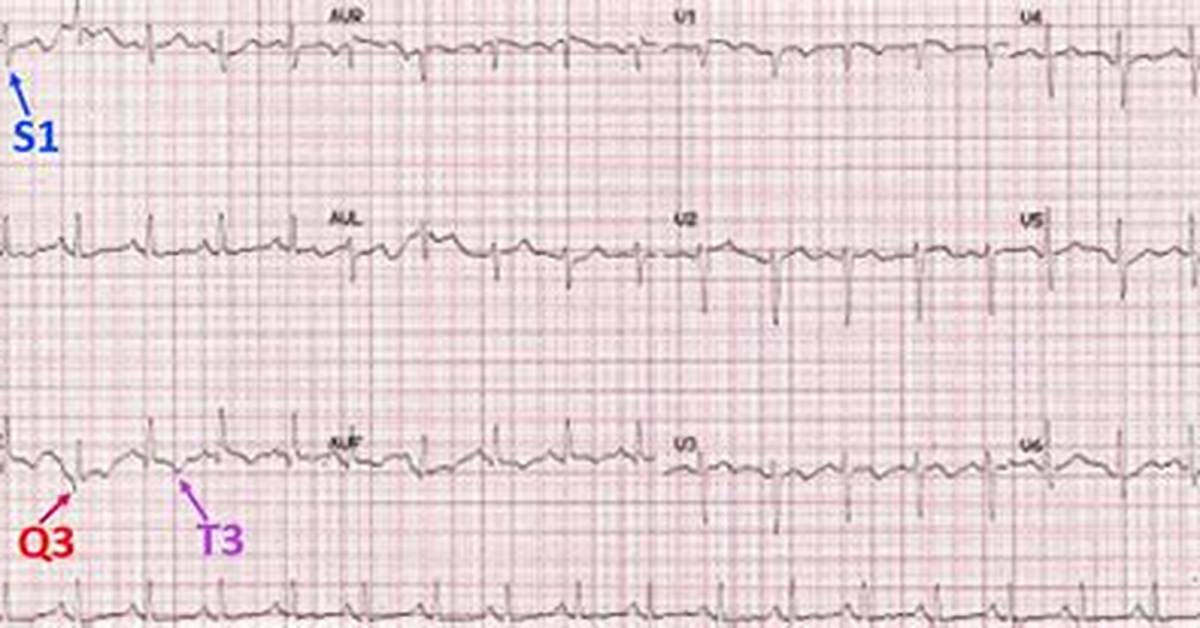
The S1Q3T3 electrocardiographic abnormality can be seen in acute bronchospasm in pregnant women. The other causes like pulmonary embolism, pneumothorax, acute lung disease, cor pulmonale, and left posterior fascicular block were excluded.
Can S1Q3T3 be normal?
A finding of S1Q3T3 is an insensitive sign of right heart strain. It is non-specific (as it does not indicate a cause) and is present in a minority of PE cases. It can also result from acute changes associated with bronchospasm and pneumothorax.
How common is S1Q3T3?
The incidence of S1Q3T3 in patients diagnosed with PE varies from as low as 10% to as high as 50%.
What are the ECG changes in PE?
ECG changes in PE are related to:
Dilation of the right atrium and right ventricle with consequent shift in the position of the heart. Right ventricular ischaemia. Increased stimulation of the sympathetic nervous system due to pain, anxiety and hypoxia.
How might you Recognise cor pulmonale on an ECG?
Electrocardiographic (ECG) abnormalities in cor pulmonale reflect the presence of right ventricular hypertrophy (RVH), RV strain, or underlying pulmonary disease (see the image below). Such ECG changes may include the following: Right axis deviation.
What is acute cor pulmonale?
Acute cor pulmonale is a form of acute right heart failure produced by a sudden increase in resistance to blood flow in the pulmonary circulation, which is now rapidly recognized by bedside echocardiography.
Is S1Q3T3 specific for PE?
The incidence of S1Q3T3 is reported to be between 12% and 50% in acute pulmonary embolism and is non-specific. This ECG abnormality can occur in the presence or absence of pulmonary embolism [17].
Is cor pulmonale right heart strain?
Cor pulmonale is a condition that causes the right side of the heart to fail. Long-term high blood pressure in the arteries of the lung and right ventricle of the heart can lead to cor pulmonale.
Does right heart strain mean cor pulmonale?
This makes it harder for the heart to pump blood to the lungs. If this high pressure continues, it puts a strain on the right side of the heart. That strain can cause cor pulmonale. Lung conditions that cause a low blood oxygen level in the blood over a long time can also lead to cor pulmonale.
Does PE show on ECG?
2 The ECG is often abnormal in PE, but findings are neither sensitive nor specific for the diagnosis of PE. 3 The greatest utility of the ECG in a patient with suspected PE is ruling out other life-threatening diagnoses (eg, acute myocardial infarction).
Does pulmonary embolism show on ECG?
ECG can be normal in pulmonary embolism, and other recognised features of include sinus tachycardia (heart rate >100 beats/min), negative T waves in precordial leads, S1 Q3 T3, complete/incomplete right bundle branch block, right axis deviation, inferior S wave notch in lead V1, and subepicardial ischaemic patterns.
Does pulmonary embolism show up in blood work?
Your doctor will order a D-dimer blood test to help diagnose or rule out the presence of a pulmonary embolism. The D-dimer test measures the levels of a substance that is produced in your bloodstream when a blood clot breaks down.
What respiratory condition leads to cor pulmonale?
The most common cause of acute cor pulmonale is typically caused by a pulmonary embolism, which is a blood clot in the lungs. Chronic cor pulmonary most commonly results from COPD.
How does cor pulmonale develop in COPD?
In response to the increased pulmonary vascular resistance (PVR) the RV gradually undergoes hypertrophy and dilatation (cor pulmonale). This increase in end-diastolic volume ie, pre-load, to maintain a normal stroke volume accounts for the reduced right ventricular ejection fraction.
How is cor pulmonale related to COPD?
Chronic obstructive pulmonary disease (COPD) is the most common cause of cor pulmonale. The severity of cor pulmonale appears to correlate with the magnitude of hypoxemia, hypercapnia, and airflow obstruction.

