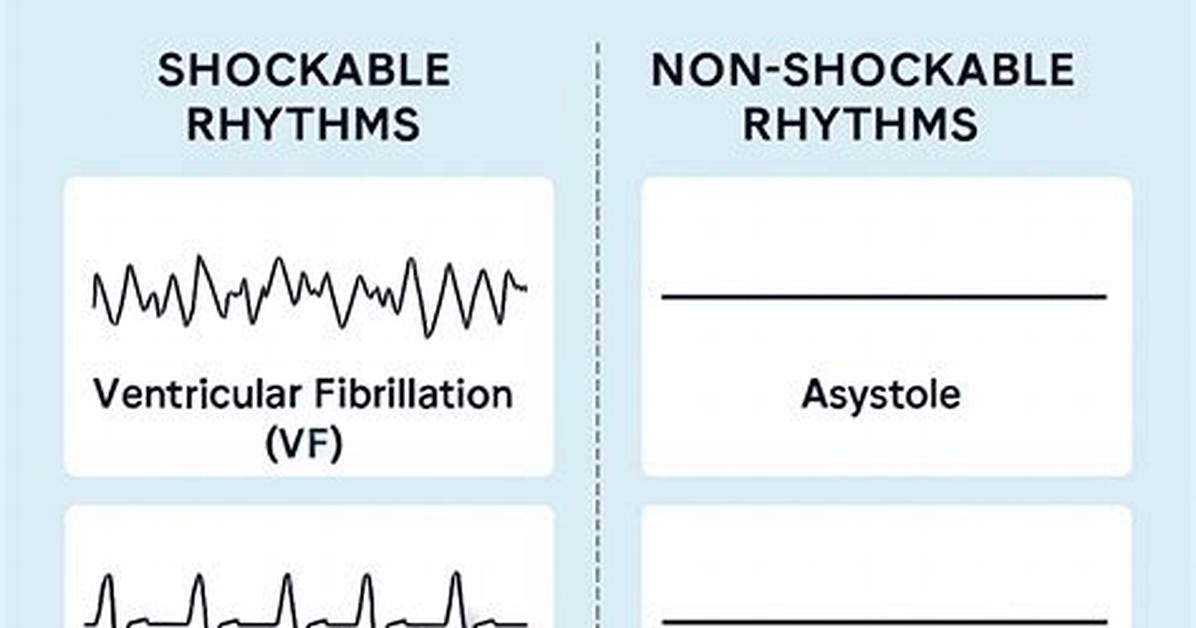
Patients in asystole are known to have a very poor prognosis, with 0% to 2% surviving to hospital discharge. There is a slightly better prognosis if the rhythm converts spontaneously to a shockable rhythm early(1). The Advanced Life Support guidelines do not recommend defibrillation in asystole.
Is AFIB a shockable rhythm?
There are two shockable rhythms and two non-shockable rhythms. The two shockable rhythms are: Ventricular Fibrillation, or VFib. Pulseless ventricular tachycardia, or V-tach.
What rhythms can be defibrillated?
Defibrillation – is the treatment for immediately life-threatening arrhythmias with which the patient does not have a pulse, ie ventricular fibrillation (VF) or pulseless ventricular tachycardia (VT).
What are the 5 lethal cardiac rhythms?
You will need to be able to recognize the four lethal rhythms. Asystole, Ventricle Tachycardia (VT), Ventricle Fibrillation (VF), and Polymorphic Ventricle Tachycardia (Torsade de pointes). Use this study guide and other resource books to review ECG interpretation.
Can you do CPR on asystole?
Asystole is a non-shockable rhythm. Therefore, if asystole is noted on the cardiac monitor, no attempt at defibrillation should be made. High-quality CPR should be continued with minimal (less than five seconds) interruption.
Do you give EPI for asystole?
Asystole Treatment Steps
Give 1mg of epinephrine as soon as possible and every 3 to 5 minutes. After two minutes of CPR, check the patient’s rhythm.
Do you shock SVT?
The shock that is delivered for SVT is synchronized to occur at a precise time during the “R” wave on the EKG, so as to avoid the vulnerable refractory period which could cause ventricular fibrillation. This is simply accomplished by pressing the “sync” button that is found on all defibrillators.
Can you shock torsades?
Pulseless torsades should be defibrillated. Intravenous magnesium is the first-line pharmacologic therapy in Torsades de Pointes. Magnesium has been shown to stabilize the cardiac membrane, though the exact mechanism is unknown.
Which is worse AFib or VFib?
Ventricular fibrillation is more serious than atrial fibrillation. Ventricular fibrillation frequently results in loss of consciousness and death, because ventricular arrhythmias are more likely to interrupt the pumping of blood, or undermine the heart’s ability to supply the body with oxygen-rich blood.
Do you defibrillate atrial fibrillation?
In simpler configurations, standard single or dual chamber ventricular defibrillators have been used for atrial defibrillation purposes. In such systems, the shock vector configuration between the ventricle and the pectoral ICD usually includes the atria and therefore, successfully terminates atrial fibrillation.
Will an AED shock ventricular tachycardia?
The AED is designed to shock VF or VT (ventricular tachycardia), which is a very weak but fast heart rhythm.
When should you Cardiovert SVT?
The symptoms listed above that would indicate the patient is unstable are noted with the letter (U). Stable but serious symptoms are indicated with the letter (S). Unstable patients with SVT and a pulse are always treated with synchronized cardioversion. The appropriate voltage for cardioverting SVT is 50-100 J.
Is SVT a lethal rhythm?
Supraventricular tachycardia (SVT) is generally not life-threatening unless you have heart damage or other heart conditions. However, in extreme cases, an episode of SVT may cause unconsciousness or cardiac arrest.
What are the 6 lethal cardiac rhythms?
You will learn about Premature Ventricular Contractions, Ventricular Tachycardia, Ventricular Fibrillation, Pulseless Electrical Activity, Agonal Rhythms, and Asystole. You will learn how to detect the warning signs of these rhythms, how to quickly interpret the rhythm, and to prioritize your nursing interventions.
What is the difference between V-tach and SVT?
Two types of tachycardia we commonly treat are: Supraventricular tachycardia (SVT) begins in the upper portion of the heart, usually the atria. Ventricular tachycardia (VT) begins in the heart’s lower chambers, the ventricles.
What drug do you give for asystole?
The only two drugs recommended or acceptable by the American Heart Association (AHA) for adults in asystole are epinephrine and vasopressin. Atropine is no longer recommended for young children and infants since 2005, and for adults since 2010 for pulseless electrical activity (PEA) and asystole.
Is atropine used for asystole?
Atropine is inexpensive, easy to administer, and has few side effects and therefore can be considered for asystole or PEA. The recommended dose of atropine for cardiac arrest is 1 mg IV, which can be repeated every 3 to 5 minutes (maximum total of 3 doses or 3 mg) if asystole persists (Class Indeterminate).
What is the difference between PEA and asystole?
Asystole is the flatline reading where all electrical activity within the heart ceases. PEA, on the other hand, may include randomized, fibrillation-like activity, but it does not rise to the level of actual fibrillation.

